
As co-founder of healthsites.io and project leader for this Digital Public Good, a UN-recognized open, global registry of health facility data on OpenStreetMap, I wanted my first post here to start with something live: how our data ended up inside an active Ebola response, and what that says about the case for funding open data infrastructure.
DRC Ebola Bundibugyo – Epidemic Intelligence Dashboard
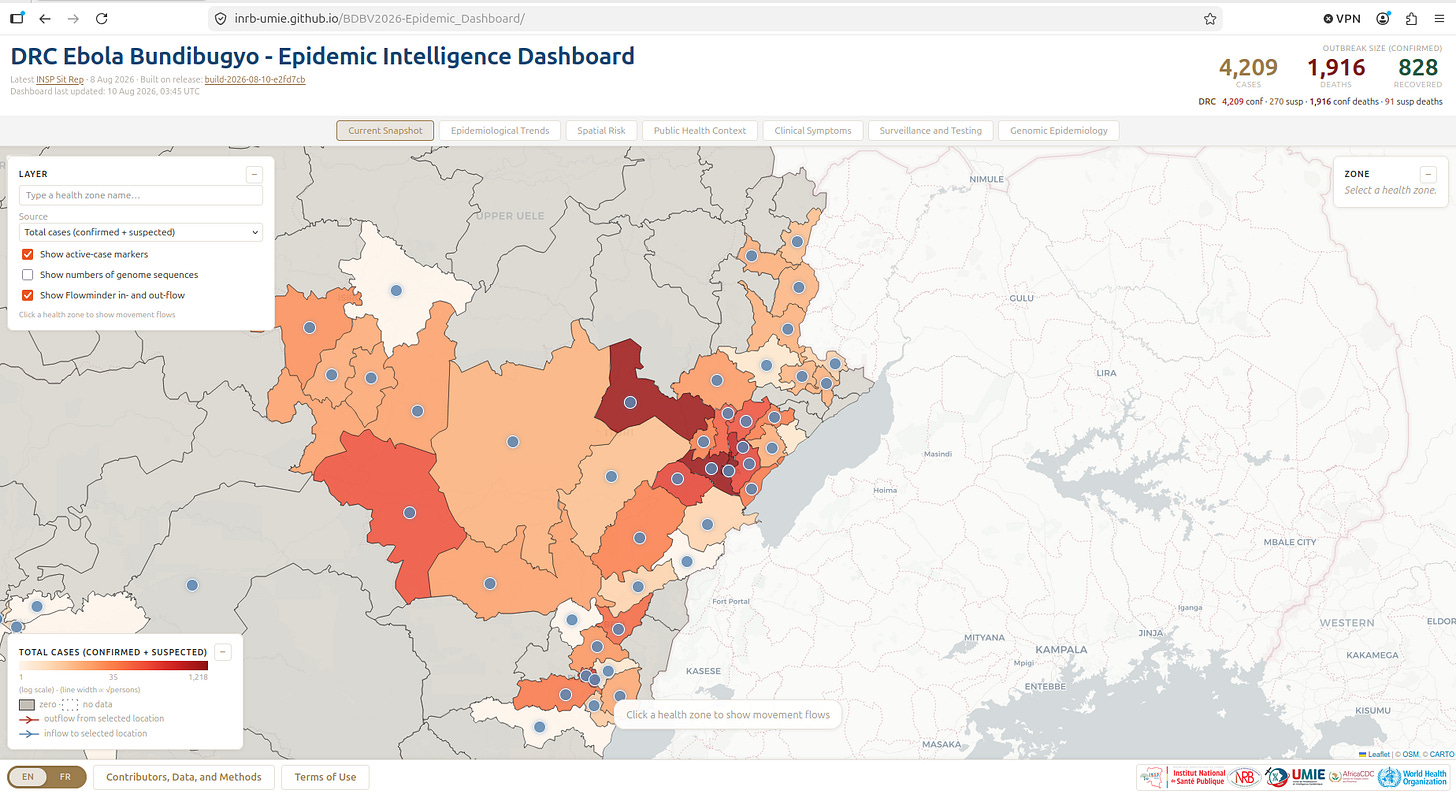
I want to walk through why that matters, and what it tells us about the model we’ve been building.
Two views of “what facilities exist” are better than one
That facility data feeds directly into core dashboard functions: which zones have testing and treatment capacity, travel time from suspected-case locations to the nearest functioning facility, and the dashboard’s spatial risk model estimating each health zone’s probability of outbreak invasion.
Part of a wider community of practice
Missing Maps’ founding principle is that people come before data, contributions are open by default, and mapping capacity gets built locally and sustainably rather than parachuted in for a single crisis. Those are the same commitments healthsites.io operates under as a Digital Public Good, and they’re what make cross-organizational validation actually work in a live response: when HOT, MSF, and healthsites.io are all mapping to the same open standard under the same shared ethics, a facility one organization adds can be checked, corrected, and reused by all the others within hours.
Driving that validation at scale is exactly what our Emergency Health Mapping campaigns are for, structured, time-boxed efforts that turn general community goodwill into a specific, checked dataset, rather than a one-off survey that goes stale the moment it’s published. More on that below.
Why open science beats a black box
That’s the open scientific method applied to a live emergency: publish your methods, publish your data, and let anyone check the work while the outbreak is still unfolding, not once it’s over. An open geospatial data model fits that naturally. It’s inspectable, reusable by any response partner without a licensing negotiation, and it can absorb new contributors, Congolese mappers, humanitarian GIS teams, local health authorities, without a gatekeeper in the loop.
That’s the same open, scientific community of practice healthsites.io was built to be part of: a UN-recognized Digital Public Good, provenance tracked on every data point, and a global, community-validated facility registry that any legitimate responder can plug into, whether the trigger is an earthquake, a disease outbreak, or routine health-system planning. We publish our own roadmap for where the platform is headed next, openly, for the same reason.
Stewardship is the actual product
A facility list is only as useful as its last update, and outbreaks are precisely when facility status changes fastest. What makes healthsites.io usable in a moment like this isn’t just that the data exists, it’s how it’s stewarded: every data point carries a sourced, auditable trail; the Ministry of Health stays the validator of record for its own national data; no personal data is collected, only facility metadata; and the data is licensed under ODbL, so it stays a public good rather than becoming anyone’s proprietary asset.
That combination, transparency, local authority, privacy by design, open licensing, is what let a consortium like INRB, INOHA, INSP, Africa CDC, and WHO build a data collaborative in support of decision making, not just a repository, and trust it enough to plan around.
The data behind the BDBV dashboard wasn’t collected *for* this outbreak. It’s cumulative, community-maintained baseline data, the same kind that came out of our Saint-Louis, Senegal emergency mapping campaign, that’s simply there, ready, the moment a response needs it. That’s the whole point of keeping a standing data collaborative alive between crises instead of rebuilding from scratch every time.
The numbers are still moving the wrong way
At the Africa CDC press briefing on August 6, 2026, Dr. Jean Kaseya laid out how far this outbreak has already outpaced precedent: by week 11, confirmed cases stood at 3,973 and deaths at 1,801, 8.4x more cases and 6.1x more deaths than the next-highest comparator outbreak at the same stage.
Africa CDC’s response now centers on seven decisions intended to reverse that trajectory:
1. Establish a village-centered response
2. Implement free healthcare and stabilize the health workforce
3. Accelerate the digital transformation of the response
4. Safeguard the reopening of schools in September
5. Develop an integrated health and humanitarian plan
6. Intensify cross-border cooperation
7. Strengthen coordination, transparency and accountability
One question from a journalist in the room stood out to me: “Which DRC-based companies, mining companies among them, are funding the response?”
No one in the room had a good answer, and that’s exactly the kind of gap open, well-provenanced facility data is built to close. It’s also a concrete opportunity: DRC-based companies with a stake in the region, mining operations very much included, could fund the specific infrastructure this response is already running on, rather than building a CSR programme from scratch.
Three items on our roadmap are open for that kind of support right now:
– **Campaign support** (Live). Structured, HCD-led Emergency Health Mapping campaigns, our validated model, that turn general community mapping goodwill into checked, field-validated facility data.
– **DRC Health Facility Data Pipeline** (Live). The managed pipeline that gets WHO, INSP, and Health Cluster facility data published to OpenStreetMap and live via API, the same pipeline feeding the BDBV2026 dashboard’s SEIR model across 519 health zones.
– **Open Identifier Infrastructure** (In development). A persistent, resolvable identifier (UUID) linking each facility across OpenStreetMap, DHIS2, and the Ministry’s own registry, the technical fix for a response where every partner currently has to join data by geographic proximity because there’s no shared key.
Request the healthsites.io data re-use strategy to see how a company operating in the DRC could plug into any of these.
If your organization needs this kind of data
This is the part I’d usually leave to a footer, but it’s the actual ask: **the same 1.18M+ facility dataset feeding the BDBV dashboard is available via API**, to any responder, researcher, or agency doing distribution logistics, provider-network verification, or cross-agency coordination.
Get free API access , or if you need higher-volume or SLA-backed access,join the premium tier waitlist. I’d genuinely like to hear what you’re building.
If you’re a Ministry of Health or institutional partner instead, we can help you validate and publish your own national facility list, with your Ministry retained as validator of record. Start a conversation.
Dig deeper
**Institutions and sources named in this piece:**
– Ministry of Public Health, Democratic Republic of the Congo
– World Health Organization (WHO)
– Africa Centres for Disease Control and Prevention (Africa CDC)
– Institut National de Recherche Biomédicale (INRB)
– Institut One Health pour l’Afrique (INOHA)
– Institut National de Santé Publique (INSP)
– BDBV2026 Epidemic Intelligence Dashboard
– The Lancet Infectious Diseases
– Africa CDC press briefing coverage, August 6, 2026 (WHO)
**More on the data and research:**
– **Underlying data and pipeline:**
– **Research letter:** “Real-time epidemic intelligence in a public health emergency: the 2026 Bundibugyo virus outbreak,” *The Lancet Infectious Diseases*
—
*A version of this piece first ran on the healthsites.io Medium publication.*


